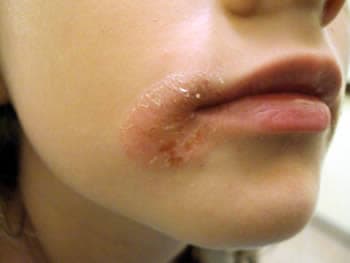
What is angular cheilitis?
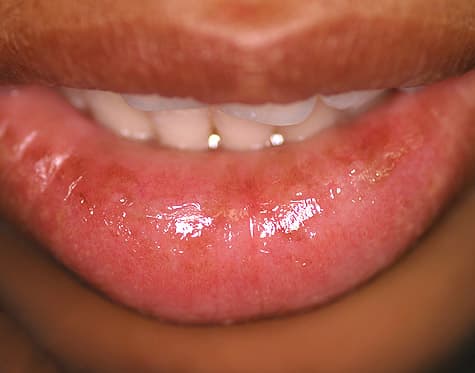
Angular cheilitis is inflammation of the skin at one or both corners of the mouth. The corners become red, sore and cracked, sometimes with blisters, crusts, oozing or bleeding, and opening the mouth wide hurts (DermNet, Cleveland Clinic). It is common at any age, from infants to older adults, and is also called angular stomatitis, perleche or cheilosis (DermNet, Cleveland Clinic).
It is not a cold sore and it is not contagious. Cold sores are caused by a herpes virus and can be passed on; angular cheilitis is a reaction of the skin to saliva and, often, to the yeast or bacteria that then settle in the cracks (Cleveland Clinic, DermNet). Depending on the cause it may clear in a few days or persist and keep coming back (DermNet).
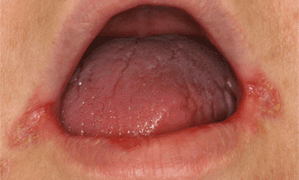
Why the corners of the mouth crack
The corner of the mouth is a hinge where the moist lining of the mouth meets facial skin, and it is in constant use for eating, drinking and talking. Saliva pools there, and the constant wet-dry cycle plus the digestive enzymes in saliva break down the skin barrier, producing an irritant eczema of the corners (DermNet, Cleveland Clinic, DermNet lip-licker's dermatitis). Once the skin is cracked, yeast (Candida) or bacteria (Staphylococcus aureus) get into the fissures and cause infection or inflammation; a swab occasionally grows the herpes virus instead (DermNet, Cleveland Clinic, PMC cheilitis classification).
Several factors make the corners stay wet or lose their shape, and most people with angular cheilitis have more than one:
- Lip licking, drooling and dribbling during sleep, thumb or dummy sucking in babies and toddlers, and face masks that trap moisture (DermNet, Cleveland Clinic).
- Deep folds at the corners: an overhanging upper lip with deep "marionette" lines, sagging skin with age, rapid weight loss, smoking (which reduces skin elasticity), a set-back lower jaw, or dentures that are worn down or ill-fitting so the face contour changes and the corners fold inwards (DermNet, Cleveland Clinic, DermNet oral candidiasis).
- Dry, chapped lips of any cause, including cold, windy, dry weather and the oral vitamin A-derived treatments used for severe acne, which dry the lips (DermNet, DermNet cheilitis, DermNet oral candidiasis, PMC cheilitis classification).
- Oral thrush, which is more likely in infancy and old age, with diabetes, after antibiotics, with steroid inhalers or tablets, and with a weakened immune system; dentures left in overnight encourage it (DermNet, NHS oral thrush, DermNet denture stomatitis).
- Nutritional deficiencies: iron, vitamin B12 or folate, riboflavin (vitamin B2), zinc or protein. Painful cracks at the corners of the mouth are a recognised sign of iron deficiency, and coeliac disease can be the hidden reason for a deficiency (DermNet, DermNet iron deficiency, NHS iron deficiency anaemia, NHS B12/folate deficiency, PMC cheilitis classification).
- Skin and general conditions: atopic eczema and other sensitive-skin types, Sjögren's syndrome (dry mouth and eyes), Crohn's disease and ulcerative colitis, diabetes, Down's syndrome, and HIV or other causes of a weak immune system (DermNet, Cleveland Clinic, NHS Sjögren's, NHS Crohn's).
- Allergy or irritation from lipsticks, lip balms and other lip-care products, cosmetics or metals (DermNet cheilitis, DermNet contact dermatitis, NHS contact dermatitis, Cleveland Clinic).
Symptoms
- Soreness, burning or tightness at the corners of the mouth, worst when you open wide or yawn, and stinging with spicy food (DermNet, Cleveland Clinic).
- Redness, swelling and small cracks or fissures running from the corner outwards; sometimes blisters, soggy whitish (macerated) skin, yellowish crusts or bleeding (DermNet, Cleveland Clinic).
- Usually both corners are affected symmetrically, but it can affect one side only (DermNet).
- On brown or black skin the corners may look pale or darker rather than red, sometimes with a darker rim, and the early changes can be more subtle (DermNet).
- Other signs that point to the cause: white patches inside the mouth and an unpleasant taste (thrush); a smooth, shiny tongue with tiredness and breathlessness (iron deficiency); pins and needles with a sore, red tongue and mouth ulcers (vitamin B12 deficiency); or a red, swollen mouth lining under a denture (NHS oral thrush, DermNet iron deficiency, NHS iron deficiency anaemia, NHS B12/folate deficiency, DermNet denture stomatitis).
Can angular cheilitis spread?
Not from person to person: it is not an infection you catch, so kissing, sharing cups or cutlery and close contact do not pass it on (Cleveland Clinic, DermNet). On your own face, angular cheilitis itself stays at or just beside the corners; what can travel is a secondary infection. If bacteria have colonised the cracks, the infection can spread onto the neighbouring skin as impetigo, with honey-coloured crusts, and that form of infection is contagious until it has been treated. If yeast is involved, thrush can appear inside the mouth or elsewhere (DermNet, NHS impetigo). Treating the infection and the angular cheilitis underneath it stops the spread (DermNet, Cleveland Clinic).
Redness that seems to travel from the corners onto the face or under the nose is usually one of two things: an impetigo-type bacterial spread as above, or a separate rash of small bumps around the mouth and nostrils, perioral dermatitis, which is a different condition with its own treatment (DermNet periorificial dermatitis, NHS impetigo). A dermatologist can usually tell them apart from the history and appearance, with a swab when needed (DermNet, Cleveland Clinic).
How long does it last, and does it come in stages?
Angular cheilitis does not have formal stages. The corner becomes dry and red, then cracks, crusts or turns soggy if it stays wet, and it can become secondarily infected (DermNet, Cleveland Clinic). With the cause addressed, improvement is usually seen within the first few days and most cases have resolved by about two weeks (DermNet, Cleveland Clinic). Mild saliva-induced cases often need nothing more than a barrier ointment, and some resolve by themselves (DermNet).
Recurrence is common, especially when the underlying factor cannot be changed (deep corner folds, dentures, dry mouth, a chronic illness); for some people it is a long-term, on-and-off condition (DermNet, Cleveland Clinic). Rarely, severe or long-neglected angular cheilitis leaves permanent scarring, weak thin skin or a change in skin colour at the corners (DermNet, Cleveland Clinic).
Conditions that look like angular cheilitis
| Condition | How it typically differs |
|---|---|
| Cold sores (herpes simplex) | Starts with tingling, itching or burning, then one or more painful blisters on or around the lips that heal within about 10 days; contagious from the first tingle until completely healed; recurrences are triggered by illness, sunshine or periods (NHS cold sores, DermNet herpes simplex). |
| Impetigo | Spreading sores that burst and leave golden-brown crusts, often around the nose and mouth of young children; very contagious until 48 hours into antibiotic or antiseptic treatment (NHS impetigo, DermNet impetigo). |
| Lip-licker's dermatitis | Redness, dryness and scaling in a band around the whole mouth, exactly as far as the tongue reaches, rather than only at the corners (DermNet lip-licker's dermatitis). |
| Perioral dermatitis | Clusters of small red bumps and pustules around the mouth, nostrils or eyes, sparing a rim of skin next to the lips; mostly young women and children, often after steroid creams (DermNet periorificial dermatitis). |
| Atopic eczema and seborrhoeic dermatitis | Atopic cheilitis is eczema of the lips in someone with dry, itchy atopic skin elsewhere; seborrhoeic dermatitis gives greasy yellowish scale on red skin in the folds beside the nose, the eyebrows and around the mouth (DermNet atopic dermatitis, DermNet seborrhoeic dermatitis). |
| Allergic contact dermatitis | Itchy, blistered or dry cracked skin within hours or days wherever a lipstick, lip balm, cosmetic or metal touched the skin; may spread beyond the contact area; confirmed by patch tests (DermNet contact dermatitis, NHS contact dermatitis). |
| Actinic cheilitis | Persistent dryness, scaling, thinning and fissuring of the lower lip in fair-skinned people with years of sun exposure; a pre-cancerous change, so a tender spot, persistent ulcer or growing lump on the lip needs a biopsy (DermNet actinic cheilitis). |
| Exfoliative cheilitis | Continuous peeling of the whole lip surface, mainly in young adults, worsened by licking, picking and biting (DermNet exfoliative cheilitis). |
| Oral lichen planus | White patches on the gums, tongue or insides of the cheeks, with burning and stinging when eating or drinking; can last several years; not contagious (NHS lichen planus). |
| Glandular cheilitis | A rare, chronic inflammation of the lip itself rather than its corners, one of the 'mainly irreversible' forms of cheilitis that needs specialist review (DermNet cheilitis, PMC cheilitis classification). |
| Secondary syphilis | A sore or papule at one corner only; a dermatologist considers it when angular cheilitis is strictly one-sided (DermNet, Cleveland Clinic). |
When to see a doctor
- The corners have not started to improve after a week of keeping them dry and using a barrier ointment, are not clear after two weeks, or keep returning (DermNet, Cleveland Clinic).
- Honey-coloured crusts are spreading onto the cheek or chin, or a child under 12 months has crusted sores around the mouth (NHS impetigo).
- Blisters appear in a cluster, or a sore has not started to heal within 10 days (NHS cold sores).
- You also have white patches or soreness inside the mouth, a sore or smooth tongue, tiredness, breathlessness, pins and needles, weight loss or bowel symptoms. These point to thrush, a nutritional deficiency or a gut condition, and need a doctor's assessment and usually blood tests (NHS oral thrush, NHS iron deficiency anaemia, NHS B12/folate deficiency, NHS Crohn's).
- There is a persistent crack, ulcer or lump on the lip itself, particularly the lower lip in someone with a lot of sun exposure (DermNet actinic cheilitis).
- You wear dentures and the corners keep splitting: a dentist can check the fit and bite (DermNet, Cleveland Clinic).
Diagnosis
Angular cheilitis is diagnosed from its appearance and your history: how long it has been there, whether one or both sides are affected, lip licking, dentures, inhalers, diet and general health (DermNet, Cleveland Clinic). A swab from the corner can show whether yeast, Staphylococcus aureus or the herpes virus is present, and blood tests check for nutritional deficiencies such as iron, B12 and folate and for illnesses such as diabetes; a skin biopsy is not usually necessary (DermNet, Cleveland Clinic). Allergic contact cheilitis is confirmed with patch tests (DermNet contact dermatitis).
Treatment
Treatment follows the cause, and in many mild cases none is needed beyond keeping the corners dry and protected (DermNet). A typical plan has three parts:
- Protect the corners. Apply a thick, plain barrier ointment such as petroleum jelly or an unperfumed emollient several times a day and at bedtime; for saliva-induced angular cheilitis this is often the only treatment needed (DermNet, Cleveland Clinic). Drink enough water and stop licking the corners (DermNet, Cleveland Clinic).
- Treat whatever has colonised the cracks. Depending on the swab or the clinical picture, a dermatologist may prescribe an antifungal cream, an antifungal mouth treatment for accompanying thrush, an antibacterial or antibiotic ointment, or, when the skin is significantly inflamed, a short course of a steroid ointment, used only as prescribed because overuse of steroid creams around the mouth is the most common trigger of perioral dermatitis; topical antiseptics are another option (DermNet, Cleveland Clinic, DermNet periorificial dermatitis). A pharmacist can advise on an antifungal mouth gel for thrush (NHS oral thrush).
- Fix the reason it started. Replace ill-fitting dentures so the face contour is restored and the corner furrows shrink, clean them daily and leave them out at night; rinse your mouth after steroid inhalers; correct a confirmed iron, B12, folate or zinc deficiency with supplements; improve blood sugar control; treat the atopic eczema or dry mouth behind it (DermNet, Cleveland Clinic, NHS oral thrush, NHS dry mouth, DermNet denture stomatitis). For deep corner folds that keep refilling with saliva, filler injections or implants to build up the corners are among the measures DermNet lists (DermNet).
Most people improve within days and are clear in about two weeks; if the corners are not better after two weeks of treatment, the cause needs another look (DermNet, Cleveland Clinic).
Self-care and preventing it coming back
- Keep a barrier ointment or plain lip balm on the corners through the day, before sleep and in cold or windy weather; choose one without fragrance or flavour, and use a lip sunscreen in summer (DermNet, DermNet cheilitis, Cleveland Clinic).
- Do not lick, pick or bite the corners; children who dribble or suck a dummy need the skin dried gently and protected with ointment (DermNet lip-licker's dermatitis, Cleveland Clinic).
- Denture wearers: remove dentures at night, brush them daily, and see the dentist if they feel loose or the bite has dropped (NHS oral thrush, DermNet denture stomatitis).
- Rinse the mouth with water after using a steroid inhaler (DermNet).
- Eat a varied diet with enough iron, B vitamins and protein; a confirmed deficiency should be treated and its cause found, not just supplemented (DermNet, NHS iron deficiency anaemia).
- Avoid harsh toothpaste, mouthwash and spicy food while the corners are sore; a cool compress eases pain (Cleveland Clinic).
- Do not use expired lip cosmetics, and stop any new lip product that coincided with the flare (Cleveland Clinic, DermNet cheilitis).
- Stop smoking: it reduces skin elasticity at the corners (DermNet, Cleveland Clinic).
How iDerma can help
If the corners of your mouth have not improved after a week of barrier care, or the problem keeps returning, you can book an online consultation. Send close-up photographs of both corners in daylight, with your mouth closed and open, and mention dentures, inhalers, lip products and any mouth or gut symptoms. An iDerma dermatologist will assess whether this looks like angular cheilitis or one of its look-alikes, suggest treatment, and say which swab, blood tests or dental review to arrange locally.