What is dyshidrotic eczema?
Dyshidrotic eczema, also called pompholyx, dyshidrosis or vesicular hand eczema, is a form of eczema that produces crops of tiny, deep-seated, intensely itchy blisters on the palms, the sides of the fingers and the soles (DermNet, NHS, AAD). The blisters are 1 to 2 mm across, often symmetrical, and settle over two to three weeks, leaving peeling, dry and sometimes cracked skin (DermNet, NHS). Most people get it only on the hands (AAD).
It is not contagious (AAD). Despite the name dyshidrosis, which refers to sweating, it is not a disease of the sweat glands (DermNet, AAD). It tends to come and go: some people have a single flare, others get new blisters every month or every year for years (AAD).
It is common. In one patch-test clinic about 20% of the people assessed for hand dermatitis had dyshidrotic eczema (DermNet). iDerma dermatologists see it regularly in photographs of palms sent in online, usually described by the patient as small itchy bumps on the hands or tiny blisters on the fingers; only an examination can confirm it.
What causes dyshidrotic eczema?
The cause is not known (DermNet, NHS, AAD). The AAD describes it as a hypersensitivity: people who get it react to something, such as a metal, an ingredient in a personal care product or a medicine, and a number of other factors trigger or aggravate flares (AAD). Usually more than one applies to the same person, so finding and removing triggers is part of the treatment (DermNet, AAD).
| Factor | What the evidence says |
|---|---|
| Atopy: eczema, hay fever or other allergic rhinitis, or asthma, in you or your close family | Raises the risk according to the AAD; DermNet notes that the evidence is mixed (AAD, DermNet). Atopic dermatitis elsewhere on the body makes it more likely (MedlinePlus). |
| Contact allergy to metals: nickel, cobalt, chromium | A recognised association. Sources of contact include jewellery, watch straps, phones, cement and cutting oil at work, and small amounts in food (DermNet, NHS, AAD, DermNet nickel). |
| Irritants and wet work: soaps, detergents, cleansers, solvents, hands wet for long periods (hairdressing, catering, cleaning, healthcare) | Irritant contact dermatitis aggravates it (DermNet, NHS). Washing the hands more than ten times a day counts as wet work (BAD). |
| Fungal infection of the feet (athlete's foot, tinea pedis) | Tinea pedis can set off a dyshidrotic-like eruption, including on the hands. According to the AAD, about a third of patients in one study cleared their hand eczema only after the foot infection was treated (DermNet, AAD). |
| Sweating, heat and humidity | Aggravate it without causing it; many people flare in spring and summer (DermNet, AAD). |
| Stress | Does not cause the condition but commonly triggers flares (AAD, NHS). |
| Sunlight (UVA) | Sun-induced flares are described in the months when UVA is strongest (DermNet, AAD). |
| Smoking, certain medicines, immunoglobulin infusions | All reported to trigger or worsen it: tobacco, a common over-the-counter anti-inflammatory painkiller, the oral contraceptive pill and intravenous immunoglobulin therapy (DermNet, AAD). |
Onset is most often between 20 and 40 years of age (AAD). DermNet finds no clear link with age or sex, while MedlinePlus notes that women seem more prone (DermNet, MedlinePlus). Children can be affected, but this is rare (AAD).
Is it an allergy?
In some people a contact allergy is part of the cause. A delayed contact allergy, most often to nickel or cobalt, can drive or maintain the blisters and is found by patch testing (DermNet, AAD, BAD). Nickel is present in most foods, so a low-nickel diet is only rarely helpful according to DermNet, although the AAD reports fewer and milder flares in metal-sensitive patients who follow a points-based low-nickel or low-cobalt diet (DermNet nickel, AAD). That is a decision to take with your dermatologist after patch testing, not a first step.
Symptoms: what dyshidrotic eczema looks like
- Itch, burning or prickling first. The skin often itches, burns or prickles before anything is visible (NHS, AAD).
- Tiny deep blisters. Clear, fluid-filled, 1 to 2 mm, set deep in the skin like tapioca pearls, on the palms, the sides of the fingers, or the soles and toes. They can merge into larger blisters and may weep (DermNet, NHS, AAD).
- Peeling, dryness and cracks. As the blisters dry over two to three weeks the skin peels, then may become dry, cracked and sore, and may bleed (NHS, DermNet).
- Changes after repeated flares. Thick, dry, constantly itchy skin with deep painful fissures, and nail changes such as pits, ridges, thickening and discolouration when blisters sit next to the nail fold (AAD, DermNet).
- On darker skin. The blisters look darker and the tapioca-like contrast is more striking; dark marks can linger after a flare (NHS, DermNet, AAD).
- Signs of infection. Yellow or green pus, yellow-brown crusts, swelling, spreading redness, red streaks running up the limb, pain, warmth or fever mean the blisters have become infected, which can progress to cellulitis (NHS, AAD, DermNet, MedlinePlus).
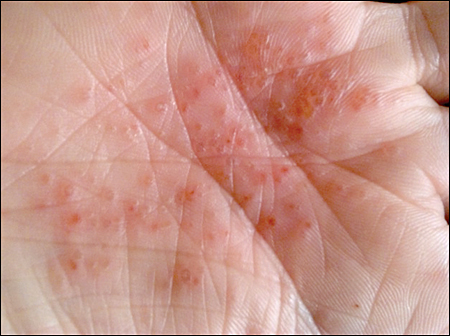
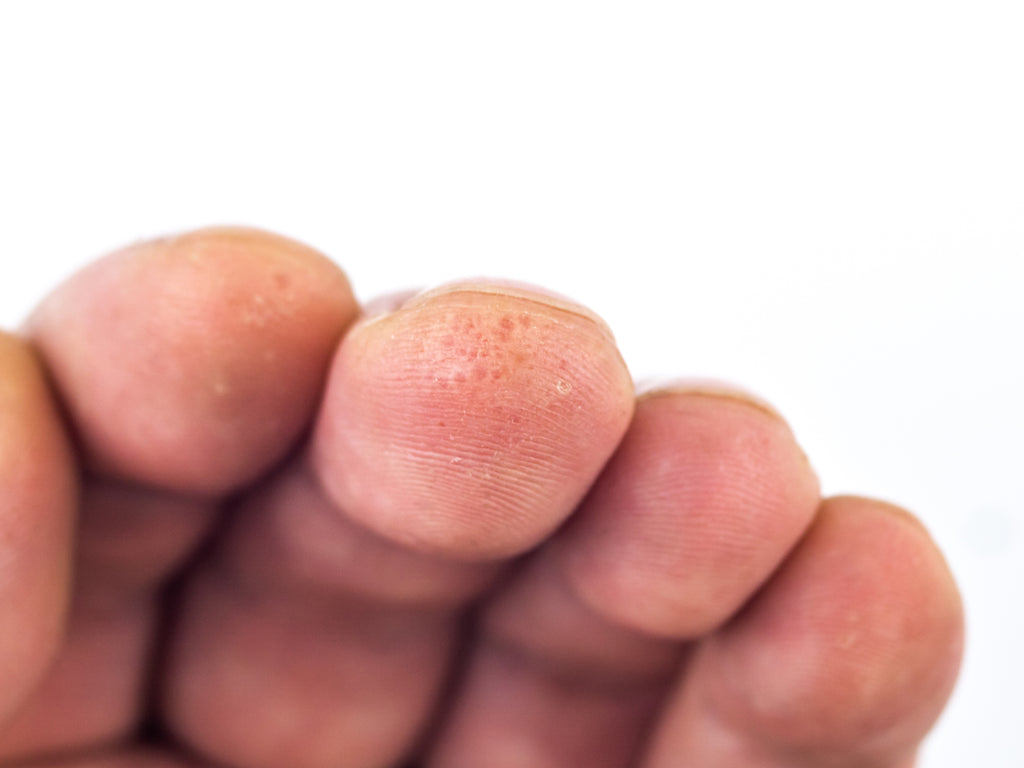
Dyshidrotic eczema: deep-seated blisters on a palm, and on the pads of the toes.
A flare typically lasts two to three weeks, sometimes up to four (NHS, DermNet, AAD). Blisters on the soles can make shoes and walking painful, and blisters on the hands can stop you using them for work until the flare settles (AAD).
Dyshidrotic eczema or something else?
Several conditions cause blisters, bumps or peeling on the hands and feet, and the treatments differ. These are the ones a dermatologist weighs up (DermNet, NHS).
| Condition | Clues that it is not dyshidrotic eczema |
|---|---|
| Athlete's foot and hand ringworm (tinea) | One-sided or asymmetrical; scaling between the toes or around the edge of the sole; blisters mainly on the inner side of the foot; skin scrapings grow fungus (DermNet tinea pedis, DermNet). |
| Contact dermatitis | The irritant type starts in the finger webs and on the backs of the hands and often spares the palms; the allergic type has a sharp edge, such as a glove-cuff line, and flares after particular tasks (DermNet hand dermatitis). |
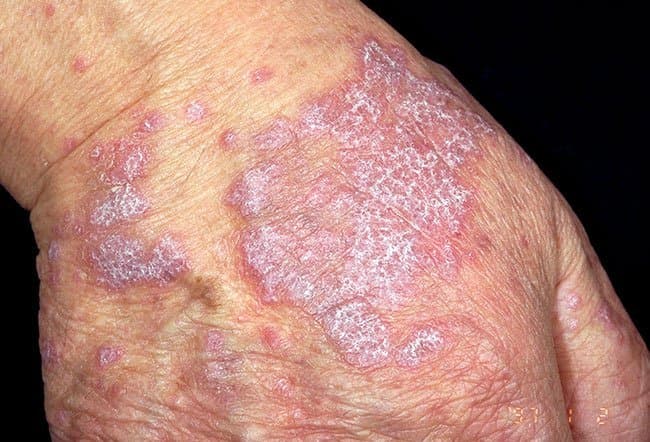
| Psoriasis of the palms and soles | Well-defined red scaly plaques rather than blisters, often with psoriasis elsewhere (DermNet hand dermatitis, BAD). |
| Palmoplantar pustulosis | Yellow pus-filled spots that turn rusty brown, within scaly patches on the palms and soles; most patients are current or former smokers (DermNet). |
| Scabies | Intense itch that is worst at night, thread-like burrows in the finger webs, wrists and palms, and a rash that also affects the wrists, waist, buttocks or thighs (DermNet scabies). |
| Exfoliative keratolysis | Superficial air-filled blisters that burst and peel in rings on the palms, with little itch; it does not respond to steroid creams (DermNet). |
| Bullous pemphigoid | An autoimmune blistering disease of older people, mostly over 50 and often over 80, that a dermatologist excludes when blisters are unusual for eczema (DermNet). |
How is dyshidrotic eczema diagnosed?
It is a clinical diagnosis: the pattern, the history and the course are usually typical once other causes have been excluded (DermNet). Tests are for the exceptions:
- Skin scrapings for fungus whenever the rash is one-sided, or when the feet are involved and athlete's foot is possible, because tinea can look identical and needs antifungal treatment rather than a steroid cream (DermNet, DermNet tinea pedis). This is done before any steroid cream is started.
- Patch testing in chronic or atypical cases, or when a contact allergy is suspected, for example after reactions to jewellery or to metals at work (DermNet, AAD, BAD).
- A swab of a blister that looks infected (AAD).
- Skin biopsy, rarely, when another blistering disease is possible (DermNet).
Tell your dermatologist about metal implants, reactions to jewellery, smoking, recent immunoglobulin infusions or vitamin injections, work with cutting oil or cement, and any new medicines (AAD).
Online, an iDerma dermatologist can usually recognise dyshidrotic eczema from close-up photographs of the palms, the sides of the fingers and the soles together with your history, and start treatment. If scrapings or patch testing are needed, you will be told exactly what to arrange locally.
How is dyshidrotic eczema treated?
Treatment aims to calm the flare, stop the itch, repair the skin barrier and prevent the next flare (NHS, AAD). It controls the condition rather than curing it (BAD, AAD). Treatments are described here by type; your dermatologist chooses the product, strength and duration.
During a flare
- Steroid creams or ointments applied for a few weeks at a time to reduce inflammation and soreness (NHS). Strong preparations are usually needed because the skin of the palms and soles is thick; used as directed, the risk of skin thinning is low (BAD, DermNet).
- Soaks and cool compresses, two to four times a day for about 15 minutes, help dry weeping blisters; a GP or dermatologist may suggest an antiseptic drying soak if the blisters leak fluid (AAD, NHS, DermNet).
- Steroid-free anti-inflammatory creams when treatment is needed often or for long periods. They may work less well than strong steroids but do not thin the skin, and can sting at first (AAD, BAD).
- Treating infection with an antibiotic course when pus, crusting or spreading redness appear (NHS, AAD).
- Itch at night: a sedating antihistamine from a pharmacist for a few nights can help sleep; non-sedating antihistamines do little for eczema itch (NHS, BAD).
- Do not burst the blisters (NHS). Scratching opens them to infection and worsens the eczema (AAD).
Between flares
- Emollients every day: after every hand wash and whenever the skin feels dry, plus an emollient soap substitute instead of soap. Choose a fragrance-free cream or ointment rather than a lotion, which contains too much water (NHS, BAD, AAD).
- Remove the trigger: protection for wet work, avoiding identified allergens and irritants, and treating athlete's foot (NHS, AAD, DermNet).
- Treat excessive sweating if the blistered skin is often wet: a prescription antiperspirant, a mild electrical-current treatment of the palms or soles (iontophoresis), or injections that switch off sweating in the treated area (DermNet, AAD).
Specialist options for severe or frequent flares
- Ultraviolet light therapy in a hospital department, typically two or three visits a week for about six weeks (NHS, BAD, DermNet).
- A short course of steroid tablets for a severe flare (NHS, DermNet, BAD).
- An oral retinoid licensed for severe long-standing hand eczema, prescribed by specialists; it must never be taken in pregnancy (NHS, BAD).
- Immune-suppressing tablets, with regular blood monitoring (BAD, DermNet).
- A newer injectable biological treatment has helped small numbers of people with hard-to-treat dyshidrotic eczema when nothing else worked (AAD, DermNet).
- A supervised low-nickel or low-cobalt diet when patch tests confirm a metal allergy (AAD); the evidence is mixed (DermNet nickel).
- Stress management, including biofeedback, where stress is the trigger (AAD).
Daily care and prevention
- Gloves for wet work: cotton gloves under waterproof gloves; take them off as soon as the task is done, dry the hands and apply emollient (NHS, AAD, BAD). Cotton gloves alone for dry tasks (AAD).
- Wash gently: lukewarm water, a fragrance-free soap substitute, no antibacterial or deodorant soaps; pat dry and moisturise straight away (NHS, AAD). Ask your dermatologist which hand sanitiser suits you (AAD).
- Rings off before washing the hands, before applying emollient and at night; moisture trapped under a ring can set off a flare (AAD).
- Feet: cotton or silk socks instead of nylon, moisture-wicking socks for sport, leather shoes instead of plastic or rubber, and shoes that are allowed to dry out (NHS, AAD).
- Barrier cream before exposure when gloves cannot be worn; wash with a soap substitute, rinse, dry and moisturise afterwards (BAD).
- At work: if irritants or wet work are unavoidable, agree with your employer on protective measures and on breaks to dry the hands and apply emollient.
- Metals: if you are nickel-sensitive, keep jewellery and metal items off the skin; a nickel test kit shows which items release free nickel (DermNet nickel).
- Heat and sweat: stay cool in hot weather and change damp socks and gloves (AAD, DermNet).
- Emollients are flammable once they soak into fabric: keep away from naked flames and wash clothing and bedding regularly (BAD).
How long does it last?
A flare lasts two to three weeks, sometimes up to four (NHS, DermNet, AAD). In most people the condition is chronic and cyclical, most active from the 20s to the 40s with fewer flares later in life; for many it eventually settles and treatment can be withdrawn (AAD, DermNet). Years of scratching can leave thickened, lichenified skin that is harder to treat (MedlinePlus).
Dyshidrotic eczema in children
Children can get dyshidrotic eczema, but it is rare (AAD). Treatment is chosen to be safe for the child's age and should be supervised by a doctor. Ask a pharmacist or doctor before giving any antihistamine to a young child (HSE).
When to see a doctor
The same day: blisters that are very painful, leak yellow or green pus or are covered in a yellow-brown crust (signs of infection), spreading redness, warmth or fever (NHS, AAD, MedlinePlus); or a sudden crop of painful blisters with fever and flu-like symptoms, which can mean a cold-sore virus infection of the eczema (BAD).
Book a dermatologist appointment if the blisters keep returning or do not settle; if itch, pain or cracks interfere with work, sleep or walking; if you suspect a metal or other contact allergy; if self-care is not working (NHS, AAD); or if you are pregnant, breastfeeding or have other conditions and need a plan that is safe for you.
An iDerma dermatologist can assess the photographs and history online, start treatment, and tell you whether scrapings, patch tests or an in-person referral are needed.
What to do now
Photograph the blisters in good light before they peel, note what your hands were doing in the days before, check your feet for athlete's foot, and start a fragrance-free emollient and glove routine today. Then book an online consultation with an iDerma dermatologist to confirm the diagnosis and get a treatment plan for flares and prevention that is matched to your triggers.