Folliculitis is inflammation of a hair follicle. It can cause tender or itchy bumps that sometimes contain pus. Infection, shaving irritation and blocked follicles are possible causes, so treatment depends on the cause. DermNet explains the different types of folliculitis.
Folliculitis can occur anywhere hair grows—from the face and scalp to the torso, buttocks, or legs. It is especially common after shaving, exercise or use of a poorly maintained hot tub. For some people, it recurs, especially if the skin continues to be irritated.
What is it?
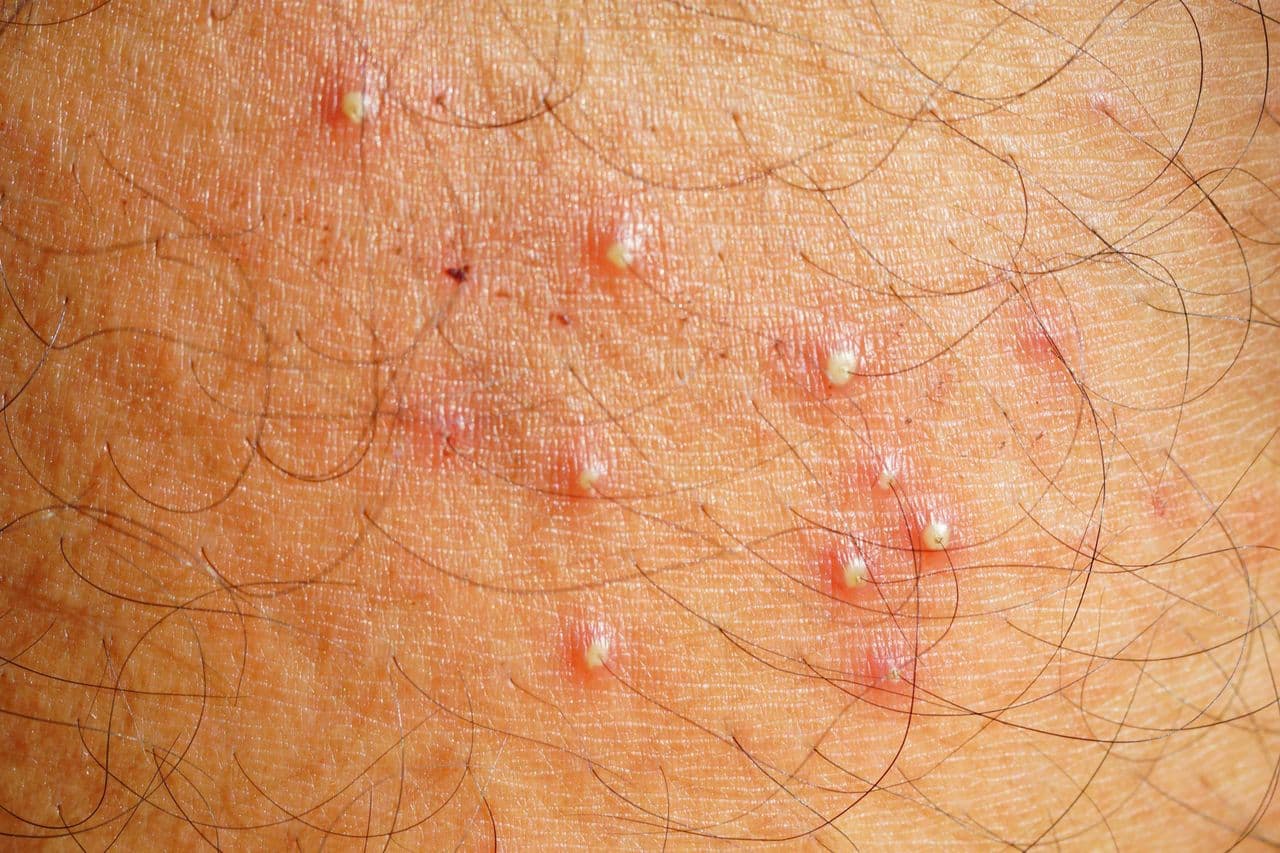
Folliculitis is an inflammatory condition characterised by papules (small bumps) or pustules (bumps with pus), centred on hair follicles. It is classified into superficial (affecting the upper layer of the follicle) and deep (inflammation involving deeper parts of the follicle). Superficial folliculitis is usually milder and short-term, while deep folliculitis can be more painful, with larger, harder inflammatory nodules, sometimes developing into boils (furuncles).
Folliculitis may have infectious origin (caused by bacteria, fungi, viruses, or parasites) or non-infectious—for example, due to mechanical irritation (friction), ingrown hairs, or clogged follicles. In areas that are shaved, "pseudofolliculitis" often occurs when ingrown hairs cause inflammatory bumps that mimic infection.
Causes and Risk Factors
Possible causes include:
- Bacteria—most commonly Staphylococcus aureus. Folliculitis can also occur after using poorly maintained hot tubs or pools, associated with Pseudomonas species ("hot tub folliculitis").
- Fungi—especially yeast, which thrive in warm, moist conditions (sweaty body areas, tight synthetic clothing).
- Viruses—less common causes, but follicle inflammation can occur on damaged or irritated skin.
- Parasites / mites—for example, Demodex mites may be involved in some cases, especially on the face.
- Non-infectious factors—friction, pressure (helmets, tight clothing), ingrown hairs after shaving or depilation, follicle blockage by cosmetic products.
Risk is increased by:
- Increased sweating and warm, moist conditions (sports, working in heat).
- Skin rubbing against tight clothing or equipment (e.g., backpack straps, protective helmets).
- Shaving against the direction of hair growth, infrequent blade changes, or dull blades, irritation from depilation.
- Skin barrier damage—micro-cracks from scratching, overly harsh exfoliants, aggressive cleansers.
- Skin care products that clog pores (comedogenic formulations), unsuitable oils.
- Health conditions—diabetes, conditions or treatments that weaken the immune system, and skin conditions such as atopic dermatitis.
- Carrying Staphylococcus aureus in the nose or on the skin, which can contribute to recurrent bacterial folliculitis.
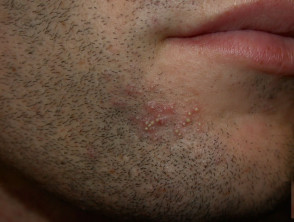
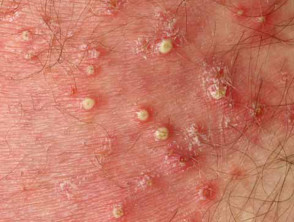
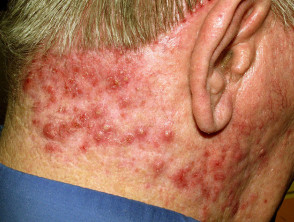
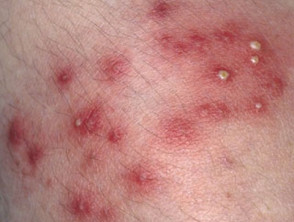
Symptoms
Main symptoms of folliculitis:
- Small red bumps or pustules, often with a hair visible in the centre.
- Itching, burning sensation, or pain.
- Sensitivity to pressure or rubbing from clothing.
- Post-inflammation—temporary hyperpigmentation (darker spots) or, in rare cases, scarring, especially after deeper folliculitis.
Commonly affected areas: face and beard area, neck, scalp, back and chest, buttocks, thighs, and calves. Hot tub folliculitis develops after exposure to contaminated water and is often worse beneath swimwear.
When to See a Doctor?
See a GP or dermatologist if:
- The rash does not subside within 1–2 weeks despite proper care.
- You develop large, deep or very painful lumps, particularly if they contain pus.
- Folliculitis recurs or spreads to new areas.
- You develop a fever, general weakness, or swollen lymph nodes.
- You have a weakened immune system, for example because of a medical condition or treatment.
- Scalp bumps are accompanied by hair loss or scarring.
Seek urgent medical advice for fever, rapidly spreading redness, severe pain or a boil on the face. For persistent or recurring bumps without these warning signs, an online dermatologist consultation can help assess the next step. An examination or skin sample may be needed in person.
Diagnosis
A doctor can usually diagnose folliculitis by examining your skin and asking when the bumps appeared and whether they followed shaving, exercise or swimming. If necessary, additional tests may be used:
- Microbiological culture from a pustule or lesion when bacterial folliculitis or frequent recurrences are suspected.
- Skin scrapings or microscopy may help identify fungal causes; other tests depend on the suspected diagnosis.
- PCR tests—for identifying specific viral agents, if indicated clinically.
- Dermatoscopy—helps differentiate folliculitis from other rashes, assess ingrown hairs.
If folliculitis recurs, the doctor may look for predisposing factors (e.g., skin barrier disorders, shaving irritation or carriage of bacteria such as Staphylococcus aureus) and work with you to develop a preventive plan.
Treatment
Treatment depends on the cause and severity of folliculitis. Mild cases may improve with skin care and avoiding triggers; others need medication.
General principles:
- Skin hygiene—gentle cleansers and washing after exercise, using a sauna or swimming.
- Reducing friction—looser, breathable clothing; change out of wet clothes promptly.
- Shaving technique—shave in the direction of hair growth, do not use dull blades, avoid shaving too close to the skin, take breaks if irritation occurs.
- Warm compresses for superficial pustular rashes—may ease discomfort.
- Do not squeeze or press pustules—this reduces the risk of scarring, pigmentation, or infection spread.
Targeted treatment (selected by the doctor, depending on the cause):
- Antiseptic washes or topical antibiotics—may be used for superficial bacterial folliculitis.
- Antifungal agents if a fungal cause is identified.
- Oral antibiotics—may be needed for severe, widespread or recurrent bacterial infection.
- For deep abscesses, the doctor may drain the abscess and prescribe further treatment if needed.
In cases of recurrent folliculitis, the doctor may recommend reviewing hair removal methods (e.g., procedures for long-term hair growth reduction) to decrease the likelihood of ingrown hairs and inflammation.
Care and Prevention
Daily habits that reduce the risk of folliculitis:
- Smart shaving—shave on clean, moistened skin, gently, in the direction of hair growth; rinse with cold water after shaving, gently dry, use non-irritating, non-comedogenic products.
- Clothing—choose breathable fabrics (cotton, technical sports fabrics that wick moisture), avoid wearing sweaty or wet clothes and swimwear for long periods.
- Sports and saunas—wash after activity, do not use shared towels, wash sportswear after each use, following the care label.
- Swimming pools—choose clean, well-maintained pools; wash after swimming; if skin is sensitive, consider shorter water exposure.
- Protecting the skin barrier—avoid aggressive exfoliation and products, choose gentle, non-comedogenic care products.
- Do not use shared hygiene items (razors, towels, sponges), regularly change razor blades.