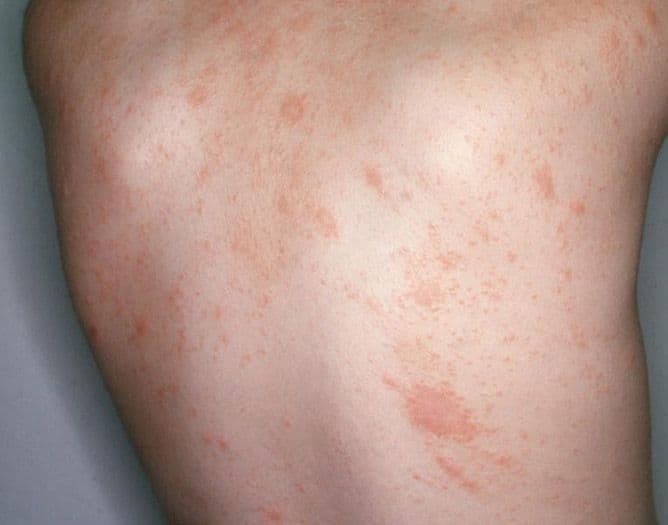
What is pityriasis rosea?
Pityriasis rosea is a common rash that is harmless for almost everyone (the exception is early pregnancy, covered below) and that runs its course and clears on its own, usually within 6 to 8 weeks (BAD, AAD). It starts with a single oval scaly patch, the herald patch, on the chest, abdomen or back. A week or two later many smaller oval patches appear across the trunk in a pattern often compared to the branches of a Christmas tree (DermNet, NHS). The name describes the rash: "pityriasis" means fine, bran-like scale and "rosea" means pink (BAD).
It cannot be passed from person to person (NHS). It is not the same condition as pityriasis versicolor, a yeast rash that is also called tinea versicolor (NHS), and it has nothing to do with rosacea despite the similar name.
Most people who get it are between 10 and 35 years old, although any age can be affected. The reported incidence is about 0.5 to 2%, and it occurs very slightly more often in women (DermNet). It may be a little more common in spring and autumn (DermNet) and has been reported in clusters in schools and families (BAD).
What causes pityriasis rosea?
The exact cause is not known (NHS). The strongest evidence points to a virus: human herpesviruses 6 and 7 have been found in the rash, blood and saliva of people with pityriasis rosea (AAD). These two viruses are not the cold-sore or genital-herpes viruses. Almost everyone catches them in early childhood; type 6 is the virus behind the toddler fever-and-rash illness roseola (DermNet roseola). The viruses then stay in the body under the immune system's control. The leading theory is that pityriasis rosea appears when that control slips for a while and the virus reactivates, although this has not been proven (AAD, DermNet).
Several points support an infection-like process: up to 69% of people have a cough, sore throat or other flu-like symptoms a few days before the rash (DermNet), the rash follows a predictable course, and a second attack later in life is rare, which suggests lasting immunity (DermNet). Other viral infections, including influenza A (H1N1) and COVID-19, have also been linked to it (DermNet).
Two things in your history matter to the doctor. A range of medicines, and some vaccines, can set off a rash that is indistinguishable from pityriasis rosea; this is why a dermatologist asks about every tablet you take and any recent vaccination (AAD, DermNet). And because the rash can occur in more than one person in a household at the same time, people often assume it is catching; it is not (MedlinePlus, NHS).
Many people ask whether stress causes it. None of the guidance pages from the NHS, the British Association of Dermatologists, the American Academy of Dermatology or DermNet lists stress as a cause or trigger. If a stressful period preceded your rash, the timing is most likely a coincidence.
Symptoms: the two stages of the rash
The rash appears in two stages (NHS).
Stage 1: the herald patch
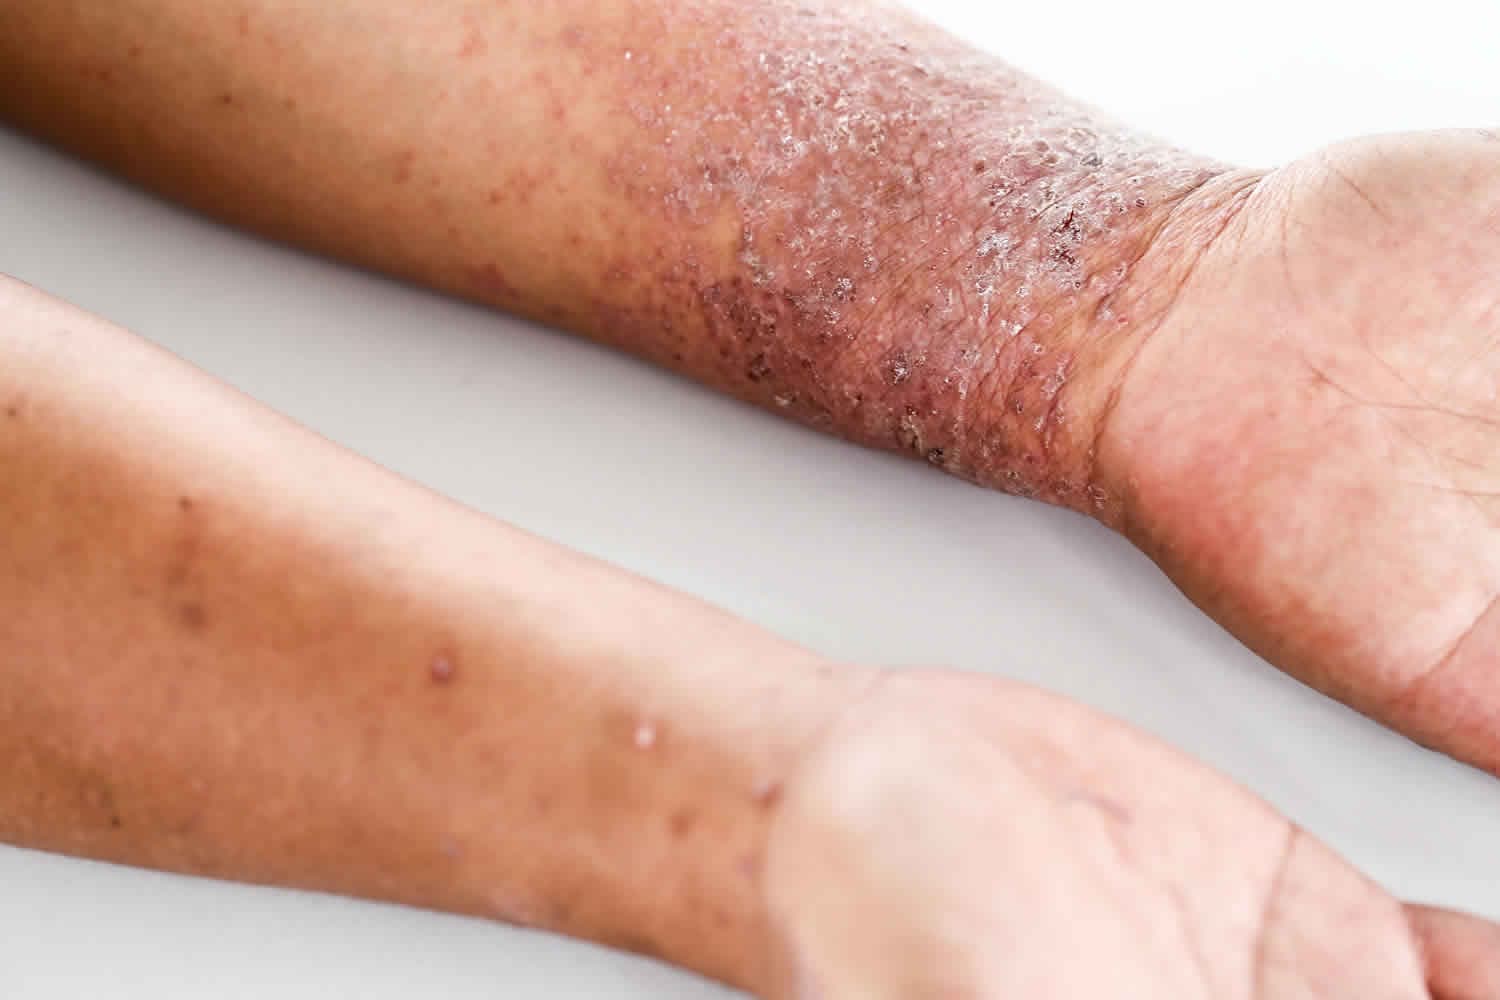
The first sign is usually a single, slightly raised, oval or round patch 2 to 5 cm across, with fine scale, on the chest, abdomen, back, upper arm, thigh or neck (NHS, DermNet). Doctors call it the herald patch or mother patch because it announces the rash to come (AAD). On white skin it is pink to salmon-coloured, often with a redder border; on brown or black skin it is usually darker than the surrounding skin, grey, violet or brown, sometimes with a lighter rim (NHS, AAD). Its scale sits just inside the edge of the patch, like a collar (DermNet). The herald patch can be mistaken for ringworm (BAD). Not everyone gets one (BAD), and rarely there are two or more (AAD).
Stage 2: the widespread rash
About 5 to 15 days after the herald patch, sometimes up to a few weeks later, many smaller oval patches appear on the chest and back and may spread to the upper arms, thighs and neck (NHS, DermNet). Their long axes follow the skin's natural tension lines, which run diagonally around the ribs, so on the back they fan out like the branches of a Christmas tree (DermNet, PCDS). Like the herald patch, each spot has a dry surface and a thin collar of scale inside its edge (DermNet). New crops appear every few days for a while, and the rash often looks worse before it starts to fade (AAD, NHS). In adults it rarely affects the face, scalp, palms or soles (DermNet, BAD).
Up to a quarter of people have itching, which can be mild or, for some, intense (DermNet); heat, sweating and hot showers make it worse (AAD). Otherwise you feel well. Flu-like symptoms, when they happen, usually come in the days before the rash rather than with it (DermNet, NHS). Rarely there are small spots or raised patches inside the mouth; these clear when the skin rash clears (AAD).
| Timeline | What usually happens |
|---|---|
| A few days before | Some people have a sore throat, cough, mild headache or tiredness (NHS, DermNet, BAD). |
| Day 0 | A single oval herald patch, 2 to 5 cm, on the trunk, neck, upper arm or thigh (NHS). |
| Day 5 to 15 | The widespread rash of smaller oval patches starts on the chest and back (NHS). |
| Weeks 2 to 6 | New crops appear; the rash may worsen before it improves (AAD, NHS). |
| Weeks 6 to 8 | Most rashes have faded (BAD, AAD); children clear faster, often in about 16 days (AAD). |
| Up to 12 weeks | Some rashes take this long (HSE); see a doctor if it is still there after 3 months (NHS, BAD). |
| Months after | Lighter or darker marks where the spots were fade slowly, especially in darker skin (NHS, AAD). |
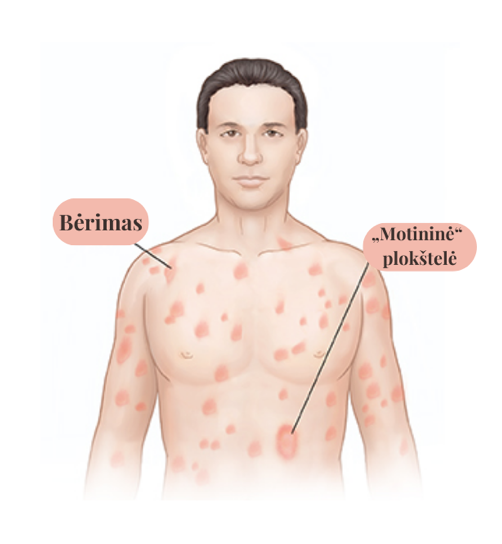
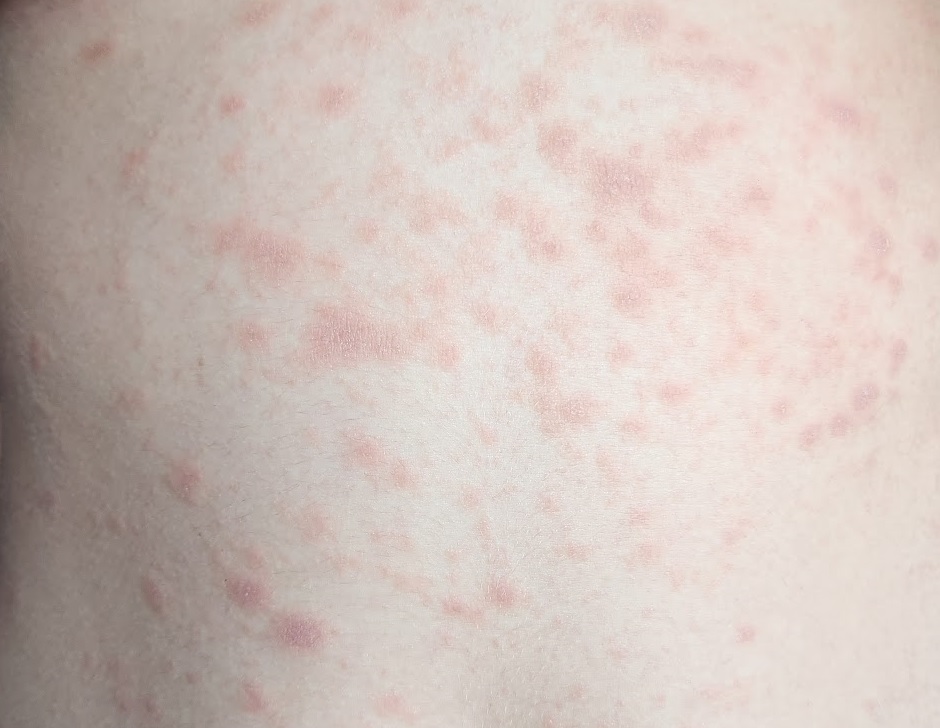
Left: a diagram of the herald (mother) patch and the trunk rash. Right: small pink oval spots across the trunk.
How it looks on different skin tones
On white skin the spots are pink or red. On brown or black skin they can be grey, dark brown or black (NHS), and the fine scale may be easier to feel than to see (HSE). After the rash has gone, many people, especially those with darker skin, are left with patches that are lighter or darker than their normal colour. These are not scars; they usually return to normal within a few months (NHS), although clearing can take 6 to 12 months and takes longest where the skin gets sun (AAD). The marks darken further with sun, so sunscreen on the affected areas helps limit further darkening while they fade (post-inflammatory hyperpigmentation, DermNet).
Atypical pityriasis rosea
Doctors call the rash atypical when it is hard to recognise (DermNet). Variants include an inverse pattern with the rash in the armpits and groin and the trunk spared, which is more common in young children and in people with deeply pigmented skin (AAD); spots that are bumpy, blistered, raised like hives, bruise-like or target-shaped like erythema multiforme; very large or merged plaques; a herald patch with no rash to follow; involvement of the mouth; a very large number of spots; or a course that drags on (DermNet). A rash on the palms and soles is a reason to question the diagnosis, because secondary syphilis affects those sites and pityriasis rosea usually does not (DermNet, PCDS).
Pityriasis rosea in children
Children get the same two-stage rash, but the pattern is more often atypical (DermNet): the face and scalp may be involved (NHS) and the inverse pattern in the skin folds is more common (AAD). Children usually clear much faster than adults, in about 16 days on average (AAD). The rash is not infectious, so there is no reason to keep a child home from school or nursery (BAD). Check with the child's doctor before giving an antihistamine, and before applying any anti-itch product to a child under 12 (AAD).
Pityriasis rosea in pregnancy
This is the situation where the rash most clearly needs prompt medical attention. In the UK the NHS advises calling your midwife, maternity unit, GP or NHS 111 immediately if you develop a new rash while pregnant, because pityriasis rosea in the first 15 weeks of pregnancy has been linked with miscarriage and premature birth (NHS, DermNet). The Irish health service advises contacting your midwife or obstetrician if you are worried (HSE). Whichever country you live in, tell your maternity team promptly about any new rash in early pregnancy. If you are or might be pregnant, see a dermatologist for a firm diagnosis so that you can tell your obstetrician (AAD). Any treatment for the itch is chosen with your pregnancy in mind, and most people need only an emollient; the point is that your pregnancy team knows about the rash and can monitor you.
Conditions that look like pityriasis rosea
Several common rashes produce oval, scaly or ring-shaped spots on the trunk, and some of them need a completely different treatment (NHS, DermNet). Do not try to diagnose it yourself; see your GP or family doctor, or a dermatologist, if you are not sure (NHS).
| Condition | How it differs from pityriasis rosea |
|---|---|
| Ringworm (tinea corporis) | One or a few rings with a raised, scaly, often bumpy leading edge, spreading slowly outwards and usually asymmetrical; itchy; a skin scraping shows fungus; it is contagious and needs an antifungal (DermNet tinea corporis, NHS ringworm). A herald patch is the classic confusion (BAD). |
| Guttate psoriasis | A shower of small drop-like pink scaly spots over the trunk and limbs, typically 1 to 2 weeks after a streptococcal sore throat; no herald patch; clears in 3 to 4 months and can turn into plaque psoriasis (DermNet guttate psoriasis). |
| Pityriasis versicolor | Flat, finely scaly patches that are paler or browner than the surrounding skin on the trunk, neck and arms, which do not tan; often comes back each summer; a yeast rash treated with antifungal washes (DermNet, NHS). |
| Secondary syphilis | A non-itchy rash of the trunk that often also involves the palms and soles, sometimes with mouth patches and feeling unwell; diagnosed with a blood test and curable with antibiotics (DermNet syphilis, NHS syphilis, PCDS). |
| Drug-induced rash | A rash that can look the same, starting after a new medicine or a recent vaccine; a dermatologist asks about both so that the trigger can be identified (DermNet, AAD). |
| Discoid eczema | Round, very itchy, inflamed coin-shaped plaques 1 to 3 cm across, often weeping or crusted, on dry irritable skin; a form of eczema that responds to emollients and anti-inflammatory creams (DermNet discoid eczema). |
| Pityriasis lichenoides | Recurrent crops of small red-brown bumps with a mica-like scale on the trunk and limbs that last months and can wax and wane for years (DermNet pityriasis lichenoides). |
| Lichen planus | Flat-topped, shiny, purple, intensely itchy bumps on the wrists, ankles and lower back, with fine white lines on their surface and often white lacy patches in the mouth (DermNet lichen planus). |
How pityriasis rosea is diagnosed
There is no laboratory test for pityriasis rosea (BAD). A dermatologist recognises the classic rash on sight: the story of a single herald patch followed a week or two later by a crop of smaller oval spots with a collar of scale along the skin lines is usually enough (BAD, AAD). A dermatoscope can help separate it from guttate psoriasis, whose dotted vessels and diffuse scale look different (DermNet guttate psoriasis).
Tests are only needed when the diagnosis is in doubt. If the herald patch could be ringworm, a scraping of scale from its edge is examined under the microscope and cultured for fungus (BAD, DermNet laboratory tests). If the palms and soles are involved, the rash does not itch, or there is any risk of a sexually transmitted infection, a blood test for syphilis is done (MedlinePlus, PCDS). If the rash is atypical or has lasted longer than two months, a small 4 mm punch biopsy under local anaesthetic can confirm the diagnosis and rule out the look-alikes (BAD, DermNet). Blood tests for the herpesviruses are not useful, because nearly everyone carries them and the commercial tests do not currently measure whether the virus is active (DermNet).
Tell the dermatologist if you are or could be pregnant, have had an organ transplant, have started any medicine in the past few months, or have recently been vaccinated (AAD). In iDerma's online consultations, the typical rash can be assessed from clear photographs of the herald patch and the trunk, taken in daylight without flash; the dermatologist will ask for a photo of the palms and soles and for your medicine list, and will tell you which test, a scraping, a blood test or a biopsy, to ask your GP or family doctor for if the picture is not typical.
When to see a doctor
- Urgently, the same day: you are pregnant and have a new rash (NHS).
- You are not sure what the rash is; a single round patch could be ringworm and scaly spots could be psoriasis or eczema (NHS, HSE).
- Itching is still troubling you after trying emollients and antihistamines from the pharmacy (NHS).
- The itch is the same or getting worse after two months (AAD).
- The rash has not gone after three months (NHS, BAD, AAD).
- The rash involves the palms, soles or mouth, does not itch at all, or you feel unwell with it (DermNet, PCDS).
- You started a new medicine or had a vaccine shortly before the rash began (AAD).
Treatment: what helps and what does not
Pityriasis rosea clears by itself, and most people need no treatment at all (BAD, AAD). Treatment aims at the itch and at speeding clearance in the minority who are severely affected (DermNet).
For mild itch: pharmacy measures
- A fragrance-free emollient applied after showering and whenever the skin feels uncomfortable softens the scale and calms the itch (NHS, AAD, BAD).
- Wash with plain water and a soap substitute instead of soap, shower gel or body wash, which dry the skin and worsen the itch (BAD, DermNet, NHS).
- Antihistamine tablets, sold without a prescription in many countries, reduce itch; a type that causes drowsiness can help if itching keeps you awake (NHS antihistamines, BAD, AAD). Ask the pharmacist which is suitable for you.
- A mild steroid cream or ointment applied twice a day to the itchiest spots if the measures above are not enough; ask a pharmacist or your family doctor which one is available where you live (BAD, NHS).
- A cool, damp cloth held on itchy skin for 3 to 5 minutes, or a lukewarm oatmeal bath, gives short-term relief (AAD).
For severe itch or a widespread, long-lasting rash: dermatologist treatment
- A stronger prescription steroid cream for a limited time (BAD, NHS).
- Narrowband UVB phototherapy, a course of carefully dosed ultraviolet light given in a dermatology department two or three times a week for about three to four weeks; in studies it reduced both itch and rash within four weeks (AAD, DermNet, HSE). Cautious natural sunlight without burning may also help the rash fade, but tanning is not advised (DermNet, MedlinePlus, AAD).
- A one-week course of an antiviral tablet for a severe or extensive rash; it can shorten the course and relieve itch, with improvement typically within 1 to 2 weeks, but it is rarely needed (DermNet, AAD, BAD).
- Steroid tablets are occasionally used for very severe itch, but routine use is not recommended because the rash can relapse when they stop and the evidence is limited (DermNet).
What does not help
- Antibiotics. Pityriasis rosea is not a bacterial infection. A class of antibiotics was once advocated and does not appear to be beneficial (DermNet); the British Association of Dermatologists notes only limited evidence and says they are rarely required (BAD).
- Antifungal creams. Never treat a suspected pityriasis rosea rash with athlete's foot or ringworm creams; they can make the rash worse (AAD). If a scraping shows fungus, the diagnosis is ringworm, not pityriasis rosea.
- Diet changes or supplements. No guidance page links the rash to food or recommends foods to avoid.
Caring for your skin while the rash lasts
- Keep cool. Heat worsens both the rash and the itch: take warm rather than hot showers, skip hot tubs and saunas, and ease off strenuous exercise that makes you sweat until the rash clears (AAD).
- Protect the rash from the sun. A sunburn on top of the rash is painful and darkens the marks it leaves; cover the rash with loose clothing or use a mild, fragrance-free broad-spectrum SPF 30 or higher sunscreen, and do not tan (AAD, DermNet). The brief, unburnt sun exposure mentioned under treatment is a different thing from tanning or burning.
- Be gentle. No scrubbing, rough sponges or exfoliants; cleanse with your hands (AAD).
- Go fragrance-free. Avoid scented, "unscented", deodorant and antibacterial soaps and lotions, which tend to irritate the rash (AAD). Fragrance-free products contain no perfume; "unscented" ones contain a masking fragrance you cannot smell.
- Wear loose-fitting clothes so nothing rubs the spots (AAD); many people find wool or rough synthetic fabrics next to the skin irritating.
- Carry on as normal. You do not need to stay away from other people, work or school (AAD, BAD). A concealer made for sensitive skin can cover visible spots (AAD).
How long it lasts and whether it comes back
Most people are clear within 6 to 8 weeks of the widespread rash appearing; DermNet gives 6 to 10 weeks, and the Irish HSE notes that the herald patch and rash together usually last 2 to 12 weeks (BAD, AAD, DermNet, HSE). A rash that lasts beyond 3 months deserves a review of the diagnosis (NHS, AAD). The spots fade without scarring; the lighter or darker marks they leave settle over months (BAD, NHS, AAD).
A second episode is unusual: recurrence is reported in about 1 to 3% of people, which fits the idea of lasting immunity after the first attack (DermNet, AAD). A different viral infection can occasionally trigger a repeat years later (DermNet).
Not sure whether it is pityriasis rosea?
If you have one oval scaly patch and are waiting to see whether more follow, if the rash is spreading beyond the trunk, or if you are pregnant and want a quick, firm answer, an online consultation with an iDerma dermatologist can usually recognise typical pityriasis rosea from photographs, judge how likely ringworm, guttate psoriasis and the other look-alikes are, and tell you which pharmacy measures are worth buying. If the pattern is not typical, the dermatologist will tell you exactly which test to ask your GP or family doctor for.
Sources: NHS, HSE, British Association of Dermatologists (BAD), Primary Care Dermatology Society (PCDS), American Academy of Dermatology (AAD), DermNet NZ and MedlinePlus; see the References list below.