What is erythema multiforme?
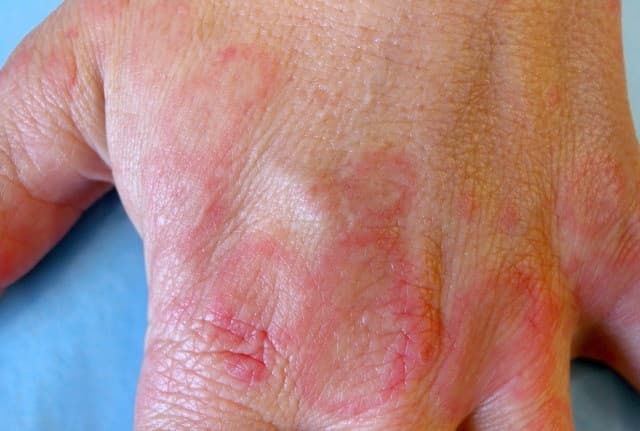
Erythema multiforme is a sudden, immune-driven reaction of the skin, and sometimes of the mouth, eyes or genitals, to a trigger that is usually an infection. Its hallmark is the "target" lesion: a round spot with a dark centre, a paler ring and a red outer rim, appearing in symmetrical crops on the hands, feet, arms and legs (DermNet, NHS). Most episodes clear on their own within 2 to 4 weeks (NHS).
The name describes the rash. "Erythema" means redness of the skin and "multiforme" means in many forms, because flat spots, raised rings, blisters and full targets can all be present in the same episode (BAD).
Doctors distinguish two forms:
- Erythema multiforme minor: skin only, or with mild involvement of one site, usually the mouth. It clears in days to weeks (BAD, DermNet, PCDS).
- Erythema multiforme major: the same skin rash plus significant, painful erosions of the mucous membranes, typically two or more sites such as the lips and mouth, the eyes or the genitals, often with fever and joint pain (DermNet, BAD, PCDS).
Erythema multiforme is a separate condition from Stevens-Johnson syndrome and toxic epidermal necrolysis. Those are rare, dangerous reactions, almost always caused by medicines, in which sheets of skin peel away (DermNet SJS/TEN). Older names such as "erythema multiforme exudativum" for Stevens-Johnson syndrome explain why some texts and search results still mix them up (DermNet SJS/TEN). The table of similar conditions below explains how to tell them apart.
Who gets erythema multiforme?
Fewer than 1 in 100 people are affected. It is most common in young adults between 20 and 40, slightly more often in men, with no link to skin colour or ethnicity (DermNet). Children and even newborns can develop it (PCDS), and in infants a vaccination is the most frequently identified trigger (DermNet). Some people carry a gene variant (an HLA type) that makes them more prone to it, with an even stronger link to the herpes-related form, and family members may have had episodes as well (DermNet, MedlinePlus). In children under 5, spots on the hands and feet are far more often hand, foot and mouth disease, a contagious viral infection described in the table further down (DermNet HFMD).
What causes erythema multiforme?
DermNet and BAD attribute about 9 in 10 cases to infection. PCDS adds that in up to half of all episodes no provoking factor is ever identified, partly because the triggering herpes infection can be subclinical. The main culprit is the herpes simplex virus, the virus behind cold sores. The rash typically appears 3 to 14 days after a cold sore, although the herpes flare can be so mild that you never notice it (PCDS). Immune cells engulf the virus and carry fragments of its DNA into the skin, where the reaction is mounted (DermNet).
Other triggers include:
- Other infections: a chest infection with a bacterium called Mycoplasma pneumoniae has long been listed as the second most common trigger (PCDS, BAD), although the eruption it causes is now increasingly classed as a separate reaction (DermNet). Chickenpox, shingles, hepatitis B and orf are also described (PCDS), as is vaginal thrush (DermNet).
- Medicines: probably fewer than 1 in 10 cases, and the evidence for many of the reported culprits is weak (PCDS). The groups most often implicated are anti-inflammatory painkillers, antibiotics, epilepsy medicines and cholesterol-lowering statins (NHS, BAD), and immunotherapy medicines (BAD). Never stop a prescribed medicine on your own. Ask the doctor who prescribed it first (NHS).
- Vaccinations: listed as a trigger by BAD, and the leading identified cause in babies (DermNet).
- Linked conditions: inflammatory bowel disease (DermNet, MedlinePlus) and lupus (MedlinePlus) are associated; DermNet notes such links mostly in persistent disease. In recurrent or persistent erythema multiforme with no clear trigger, a check for an underlying cancer is advised (DermNet).
Sunshine matters indirectly, because it is a well-known trigger of cold sores, so sun protection helps people whose episodes follow herpes (BAD, NHS cold sores).
Erythema multiforme on the hands and feet
The rash has a strong preference for the far ends of the limbs. It usually starts on the hands and feet, then involves the palms, forearms and lower legs, and spreads towards the trunk over a few days (DermNet, BAD, PCDS, DermNet herpes simplex). The upper limbs are affected more often than the lower (PCDS). The face is involved in some people, with BAD describing it as often affected and PCDS as less commonly involved, and the trunk is reached last as the rash spreads upwards (BAD, PCDS). Both sides are affected in a mirror-image pattern (DermNet, MedlinePlus).
New spots can also appear where the skin has recently been knocked, scratched or rubbed, a feature called the Koebner phenomenon (PCDS).
As a rule of thumb, a new symmetrical rash of ring-shaped spots on the backs of both hands and both feet, 3 to 14 days after a cold sore or another infection, puts erythema multiforme high on the list (PCDS). The same sites in a child under 5, with mouth ulcers, fever and small grey blisters, point towards hand, foot and mouth disease (DermNet HFMD, NHS HFMD).
What the rash looks like, step by step
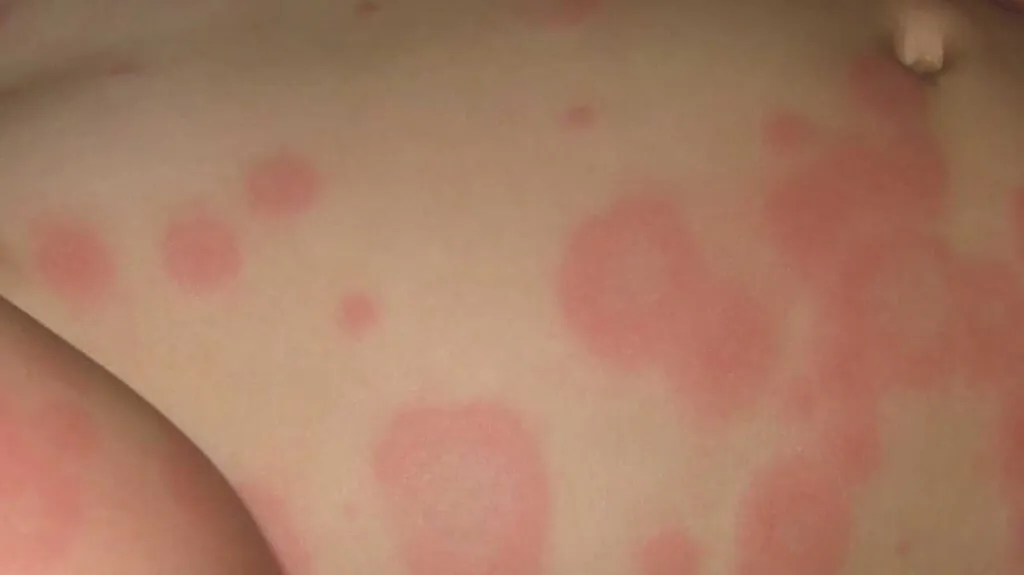
- The first days: small, round, pink or red spots appear suddenly, often in successive crops over 3 to 4 days (BAD, PCDS). They may itch or burn, or cause no symptoms at all (BAD, NHS).
- Over the following days: many spots grow into raised, well-defined discs 1 to 3 cm across and develop the classic three zones: a dusky or blistered centre, a paler swollen ring and a red outer edge (DermNet, PCDS). Some lesions show only two rings, neighbouring targets can merge into scalloped shapes, and in severe episodes hundreds of lesions at different stages are present at once (DermNet, PCDS).
- Weeks 2 to 4: each lesion fades within about two weeks and the whole episode settles in 2 to 4 weeks, or up to 6 weeks in severe cases (PCDS, NHS, DermNet). Flat darker marks may remain for several months, but the skin does not scar (DermNet).
Depending on your skin tone, the rash looks red, pink, purple or simply darker than the surrounding skin (NHS). Blisters can form in the centre of a target and, in severe episodes, burst to leave red, oozing areas (BAD).
Mouth, eyes, genitals and general symptoms
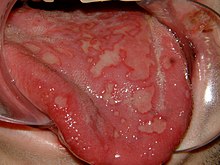
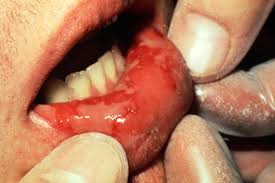
The mouth is the most commonly affected mucous membrane: redness, blisters and painful erosions on the lips, the palate and the inside of the mouth, often sparing the gums, and in the major form bloody crusts on the lips (PCDS, DermNet). Eating, drinking and brushing your teeth become painful. The eyes can become red, sore and sensitive to light, sometimes with discharge or blurred vision (BAD, MedlinePlus), and genital soreness can make passing urine painful (BAD, NHS). Mucosal lesions may appear before, together with or after the skin rash (DermNet).
Some people feel tired, achy or feverish in the days before the rash. DermNet notes that these symptoms probably belong to the infection that triggered the episode, and PCDS describes any warning symptoms in the common form as usually absent or mild. In erythema multiforme major, fever, headache and joint pain are more pronounced and you may feel unwell for a few days before the spots appear (BAD).
Minor or major: a quick comparison
| Feature | Erythema multiforme minor | Erythema multiforme major |
|---|---|---|
| Skin | Typical targets on the hands, feet, arms and legs | Spots usually larger and running into each other, with large blisters |
| Mucous membranes | None, or one mild site (usually the mouth) | Severe, painful erosions of two or more sites; crusted lips |
| General symptoms | Usually absent or mild | Fever, headache, joint pain, feeling unwell |
| Usual care | At home, symptom relief | May need hospital care for fluids, pain relief, dressings and an eye specialist (ophthalmologist) |
| Outcome | Full recovery, usually within 2 to 4 weeks | Full recovery is usual; rare scarring of the mouth or eyes |
Sources: BAD, DermNet, PCDS.
Is erythema multiforme contagious?
No. Erythema multiforme is a hypersensitivity reaction of your own immune system (BAD, MedlinePlus), so the rash itself cannot be passed to anyone else. What can spread is the trigger: a cold sore is contagious from the first tingle until it has fully healed (NHS cold sores), and a child with hand, foot and mouth disease, which also causes spots on the hands and feet, is infectious until the blisters have healed, usually 7 to 10 days (DermNet HFMD). So there is no reason to stay away from work, school or other people because of the rash itself.
What else looks like erythema multiforme?
Ring-shaped red rashes on the hands and feet have several causes. The table lists conditions that can resemble erythema multiforme and the features a dermatologist uses to tell them apart.
| Condition | How it differs from erythema multiforme |
|---|---|
| Hives (urticaria) | Very itchy weals that change shape, each of which disappears within 24 hours without leaving a mark (DermNet urticaria). A target of erythema multiforme stays fixed in place for days (PCDS). |
| Hand, foot and mouth disease | Mostly children under 5. Small grey blisters on the hands and feet and in the mouth, after a fever and sore throat. Caused by an enterovirus and contagious for 7 to 10 days (DermNet HFMD, NHS HFMD). |
| Fixed drug eruption | One or a few round, purplish patches that come back in exactly the same spot, often on the hands, feet, lips or genitals, within hours of taking a particular medicine (DermNet FDE). |
| Stevens-Johnson syndrome / toxic epidermal necrolysis | Starts with a flu-like illness, then a painful rash that begins on the trunk, spreads to the face and limbs within hours to days and peels in sheets. Nearly always caused by a medicine. A medical emergency (DermNet SJS/TEN, NHS SJS). |
| Erythema migrans (Lyme disease) | Usually a single, slowly expanding ring around a tick bite, appearing 1 to 4 weeks after the bite and lasting several weeks (NHS Lyme). |
| Granuloma annulare | Smooth, skin-coloured to pink rings over the knuckles and joints that usually cause no symptoms, although they can be tender when knocked; most clear by themselves within months, though some persist for years (DermNet GA). |
| Polymorphic light eruption | A rash on sun-exposed skin that appears within hours to 2 days of sunlight, mostly in spring and early summer, sometimes with target-like spots, and resolves faster once further sun is avoided (DermNet PMLE). |
Related articles on this site cover vasculitis, insect bites and erythema nodosum; the last is a different reaction despite the similar name.
When to see a doctor
See a doctor whenever you think you have erythema multiforme, and again if it keeps coming back, because treating the trigger may stop the cycle (NHS).
Get same-day medical help if (NHS):
- the rash involves the mouth, lips, eyes, genitals or anus;
- you find it difficult to eat, drink or pass urine;
- you have a high temperature, body aches or chills;
- the rash started after you began a new medicine.
Call 112 (the European emergency number; 999 also works in the UK and Ireland) or go to the emergency department if (NHS, NHS SJS):
- your lips, mouth, tongue or throat swell suddenly, or you struggle to breathe or swallow;
- the rash spreads rapidly, the skin is painful, large blisters form, or the skin peels in sheets;
- you suddenly become very confused, drowsy or dizzy, or someone faints and cannot be woken.
Eye symptoms of any kind, including redness, pain, discharge or light sensitivity, need an eye specialist the same day, because untreated eye involvement can leave lasting damage to sight (DermNet, PCDS). A child with a rash in the mouth or eyes, or who refuses to drink, needs same-day review; a child who is unusually drowsy, limp or floppy, or not responding normally, needs emergency care (NHS).
How erythema multiforme is diagnosed
In most people the diagnosis is made by looking at the rash and asking about the previous two weeks: cold sores, a sore throat or chest infection, new medicines and vaccinations (DermNet, BAD, PCDS). There is no single test that proves it (BAD). Because the diagnosis rests on the appearance and the story, iDerma's dermatologists assess the typical skin-only picture from clear photographs of both hands, both feet and any other affected areas, together with your timeline, and refer you for examination in person whenever the picture is not typical.
Tests are used when the picture is unclear or the rash keeps returning (DermNet, BAD):
- Blood tests: a full blood count and antibody tests for the infections that can trigger it.
- Swab or blood test for herpes simplex: recommended for everyone with recurrent episodes, including a swab from a skin or mouth lesion, because the herpes flare can be invisible (DermNet, BAD).
- Skin biopsy: a small sample taken under local anaesthetic to exclude autoimmune blistering diseases and other conditions that resemble it. Typical findings are swelling in the upper dermis and scattered dying cells in the epidermis (DermNet, BAD).
- Eye examination: whenever the eyes are red or sore.
In repeated or long-lasting episodes with no obvious cause, your doctor may also look for an underlying condition such as inflammatory bowel disease or, rarely, a cancer (DermNet).
How erythema multiforme is treated
Most episodes need no specific treatment and clear within 2 to 4 weeks (DermNet, NHS). Treatment aims to relieve symptoms, remove the trigger, protect the mouth and eyes and prevent further episodes (DermNet, BAD).
- Treat or remove the trigger. A suspected medicine is stopped by the prescriber and avoided in future (BAD, DermNet). An infection is treated on its own merits, although treating a single cold sore does not noticeably shorten that episode of erythema multiforme (DermNet).
- Itch and discomfort. Moisturisers, cool compresses and, where needed, a short course of a steroid cream or antihistamine tablets chosen by your doctor (NHS, DermNet, MedlinePlus).
- Mouth care. Antiseptic or numbing mouthwashes, soft and lukewarm food, gentle toothbrushing (DermNet, MedlinePlus). If the lips and mouth are badly affected, regular mouth-opening exercises help prevent tightening as the lining heals (BAD).
- Eye care. Prompt review by an eye specialist (DermNet, PCDS).
- Severe or major disease. Hospital care may be needed for fluids, pain relief, wound dressings and nutrition. A short course of steroid tablets is sometimes given early (BAD), and other immune-suppressing tablets are reserved for cases that are difficult to treat (BAD, DermNet). The evidence for steroid tablets is limited and their role is debated, so the decision is made case by case (DermNet, PCDS).
- Infected skin. Raw areas can pick up bacteria and may then need an antibiotic (BAD, MedlinePlus).
Recurrent erythema multiforme
Some people, especially those whose episodes follow cold sores, have several attacks a year (BAD). The standard approach is a small daily dose of an antiviral tablet taken for at least 6 months, and often for 1 to 2 years, to keep the herpes virus suppressed (BAD, DermNet, PCDS). It is offered even when no cold sore is ever seen (DermNet, PCDS). Remission can take time; a longer course or a different antiviral may be needed, and antiviral-resistant cases are sometimes treated with other immune-suppressing tablets, with variable evidence (BAD, DermNet).
Practical steps that reduce the triggers (BAD, NHS cold sores):
- Use a sunscreen lip balm (SPF 15 or higher) and sunscreen on the face when you are out in the sun, and avoid sunbeds.
- Keep a diary of each episode: infections, new medicines, vaccinations and sun exposure in the previous two weeks.
- Keep a written list of any medicine suspected of causing an episode and tell every doctor who treats you.
- At the first tingle of a cold sore, start the plan you agreed with your dermatologist.
Looking after your skin at home
- Keep the skin comfortable: a fragrance-free moisturiser, cool moist compresses on itchy or burning areas, loose soft clothing (NHS, MedlinePlus).
- Protect raw areas: do not pick or burst blisters; keep broken skin clean and covered with a protective dressing, because raw areas can become infected (BAD, MedlinePlus).
- Eat and drink enough if the mouth is sore: cool, soft, non-acidic food and plenty of fluids. When hospital care is needed, it is mostly to support eating and drinking (DermNet).
- Washing and exercise are fine if you feel well. Our dermatologists' practical advice: short, lukewarm showers, no scrubbing, no swimming pools while you have open erosions, and light exercise only.
What to do now
If you suspect erythema multiforme, photograph the rash in daylight today, write down any cold sore, infection, vaccination or new medicine from the past two weeks, and check your mouth and eyes. A skin-only rash with no fever and normal eating can be assessed by iDerma's dermatologists through an online consultation: you upload the photos and your timeline, and the dermatologist advises on symptom relief, which tests are worth doing and whether a trigger needs attention. If any of the same-day or emergency signs listed above are present, you need to be examined in person. If this is your second or later attack, book a follow-up once it has settled, because preventive treatment can stop the cycle.